

Reconstructive Urology & Urethral Stricture Care | Aligarh
Urethral Stricture: Symptoms, Diagnosis & Treatment Options

Detailed assessment of stricture location and length
Endoscopic and reconstructive treatment pathways

Recurrent-stricture and urethroplasty evaluation

In-person and online report-review options
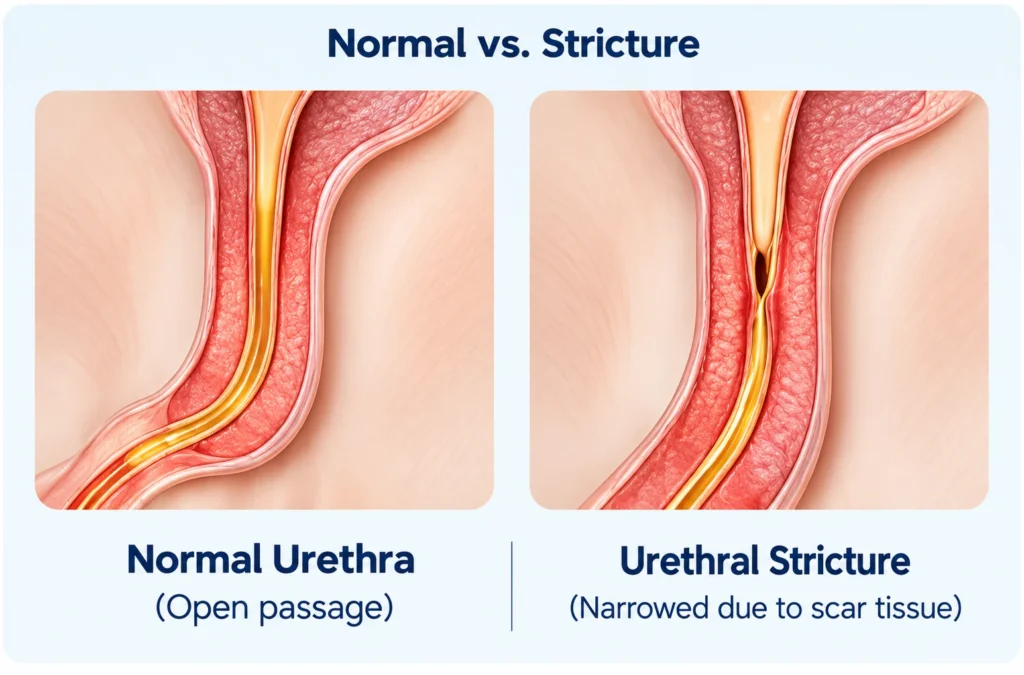
What Is a Urethral Stricture?

--- Symptoms & Warning Signs ---
Common Symptoms of Urethral Stricture
✓ Weak or slow urinary stream
✓ Difficulty starting urination or needing to strain
✓ Spraying, splitting or dribbling of the urine stream
✓ Feeling of incomplete bladder emptying
✓ Frequent urination or waking at night to pass urine
✓ Recurrent urinary infections, burning or episodes of urinary retention
--- Causes & Risk Factors---
Why Urethral Strictures Develop
✓ Previous urethral instrumentation, catheterisation or endoscopic procedures
✓ Perineal / straddle trauma or pelvic-fracture urethral injury
✓ Inflammation or previous infection affecting the urethra
✓ Lichen sclerosus and other inflammatory scarring conditions
✓ Previous pelvic or prostate treatment, including selected surgery or radiation
✓ Previous hypospadias repair or other urethral surgery; in some patients no clear cause is identified
--- Diagnosis & Evaluation---
How Urethral Stricture Is Evaluated

Clinical history and focused examination – symptoms, prior procedures, trauma, catheterisation, infections and previous operative records are reviewed.

Urinalysis and urine culture when infection is suspected – infection should be identified and managed before elective intervention when appropriate.

Uroflowmetry with post-void residual measurement – helps assess the urinary flow pattern and whether significant urine remains after voiding.

Urethrography – retrograde urethrogram (RUG), sometimes combined with VCUG, may be used to define the site, length and severity of the narrowing.

Cystoscopy / urethroscopy when clinically appropriate – allows direct visual assessment and may clarify anatomy when combined with imaging.

--- Does Every Urethral Stricture Need a Procedure? ---
Treatment Depends on Symptoms, Anatomy and Previous Care
✓ Severity of urinary symptoms and impact on daily life
✓ Stricture length, location and degree of narrowing
✓ First-time versus recurrent disease
✓ Prior dilation, DVIU, balloon treatment or urethroplasty
✓ Bladder emptying, post-void residual and infection status
✓ Patient goals, general health and reconstructive considerations
---Urethral Stricture Treatment Options ---
From Endoscopic Treatment to Reconstructive Surgery

Observation / Follow-up
For selected patients with limited symptoms or incidentally detected narrowing, depending on clinical assessment.
Urethral Dilation
Gradual widening of the narrowed segment. It can be appropriate for selected strictures but recurrence may occur.

DVIU / Internal Urethrotomy
An endoscopic incision of scar tissue performed under direct vision. Best suited to selected patterns rather than repeated use for every recurrence.
Urethroplasty
Reconstructive surgery that removes or reconstructs the narrowed segment. Technique depends on location, length, cause and prior treatment.

Alternative / Staged Reconstruction
Selected complex, lichen-sclerosus-related, post-traumatic or multiply operated strictures may require grafts, staged reconstruction, perineal urethrostomy or another specialised pathway.

Drug-Assisted Balloon Treatment
Drug-coated or drug-assisted balloon approaches may be considered in selected recurrent / short strictures depending on anatomy, evidence, availability and local regulatory context. Prezilume Therapy has a dedicated page for selected short strictures.

Comparing Common Treatment Pathways
AUA guidance advises offering urethroplasty rather than repeated endoscopic management for recurrent anterior urethral strictures after failed dilation or DVIU, and supports selected use of drug-coated balloon treatment for recurrent bulbar strictures under its specified criteria. Individual practice must also consider local availability, regulation and patient factors.
| Option | Typical Role | Important Limitations / Considerations |
|---|---|---|
| Dilation | Selected short / uncomplicated narrowing or situations where endoscopic management is reasonable. | Recurrence can occur; repeated procedures may not be the best long-term pathway for recurrent anterior strictures. |
| DVIU | Selected endoscopic treatment, particularly for suitable short bulbar strictures. | Outcomes depend on anatomy; repeated DVIU for recurrent disease may delay definitive reconstruction. |
| Drug-Assisted Balloon | Selected strictures where a drug-assisted balloon approach is clinically appropriate. | Evidence and indication vary by technique / device. Do not treat different drug-balloon approaches as interchangeable. |
| Urethroplasty | Definitive reconstructive option for many recurrent, long, penile or complex strictures. | Requires reconstructive planning, anaesthesia and procedure-specific recovery; technique varies by anatomy. |
--- Recurrent & Complex Strictures ---
When Reconstructive Urology Becomes Important
✓ Excision and primary anastomosis for selected short strictures when appropriate
✓ Substitution urethroplasty using oral / buccal mucosa grafts in suitable cases
✓ Staged reconstruction for selected complex or scarred tissues
✓ Perineal urethrostomy or other individualised options for selected complex cases
--- Before & After Treatment ---
Planning, Recovery & Follow-Up Vary by Procedure
--- Urethral Stricture in Special Situations ---
Some Strictures Need a More Individualised Reconstructive Plan
✓ Lichen sclerosus – inflammatory scarring can affect treatment choice and tissue selection.
✓ Pelvic-fracture or traumatic strictures – the anatomy and gap must be defined before reconstruction.
✓ Radiation-associated strictures – healing, continence and tissue quality require careful counselling.
✓ Post-hypospadias or previously reconstructed urethras – prior surgery may make reconstruction more complex.
✓ Recurrent strictures after multiple endoscopic procedures – re-staging the disease may be more useful than repeatedly treating the same narrowing.
✓ Female urethral stricture – uncommon and evaluated differently; management follows a separate female-urology pathway.
--- Urethral Stricture Care with Dr. Parwez Alam ---
A Structured Approach to Stricture Evaluation and Treatment
✓ Consultation & history review
✓ Diagnostic confirmation and stricture mapping
✓ Discussion of endoscopic, balloon-assisted and reconstructive options
✓ Individual treatment plan and procedure-specific counselling
✓ Follow-up for urinary symptoms, flow and recurrence monitoring
--- Online, Outstation & International Consultation---
Have Previous Stricture Reports? Start with a Structured Review
Selected outstation and international patients can arrange an online consultation to review existing reports and understand what additional evaluation may be needed before travelling. A remote review cannot replace physical examination or procedure-specific testing when those are required.

Review of previous RUG / VCUG or cystoscopy reports when available

Discussion of prior dilation, DVIU, balloon treatment or urethroplasty records

Pre-visit guidance on which reports and operative notes to carry

Second-opinion discussion for recurrent or complex urethral stricture
